Research
Theoretical architecture, candidate mechanisms, and the Gemelli/Komen clinical programme.
Mindtrek proposes a nature-based integrative approach in which the natural environment functions not as a restorative backdrop and not as a relational third party, but as a direct epistemic mirror — a field in which certain mental mechanisms become perceptible through direct engagement, rather than through symbolic interpretation of the landscape.
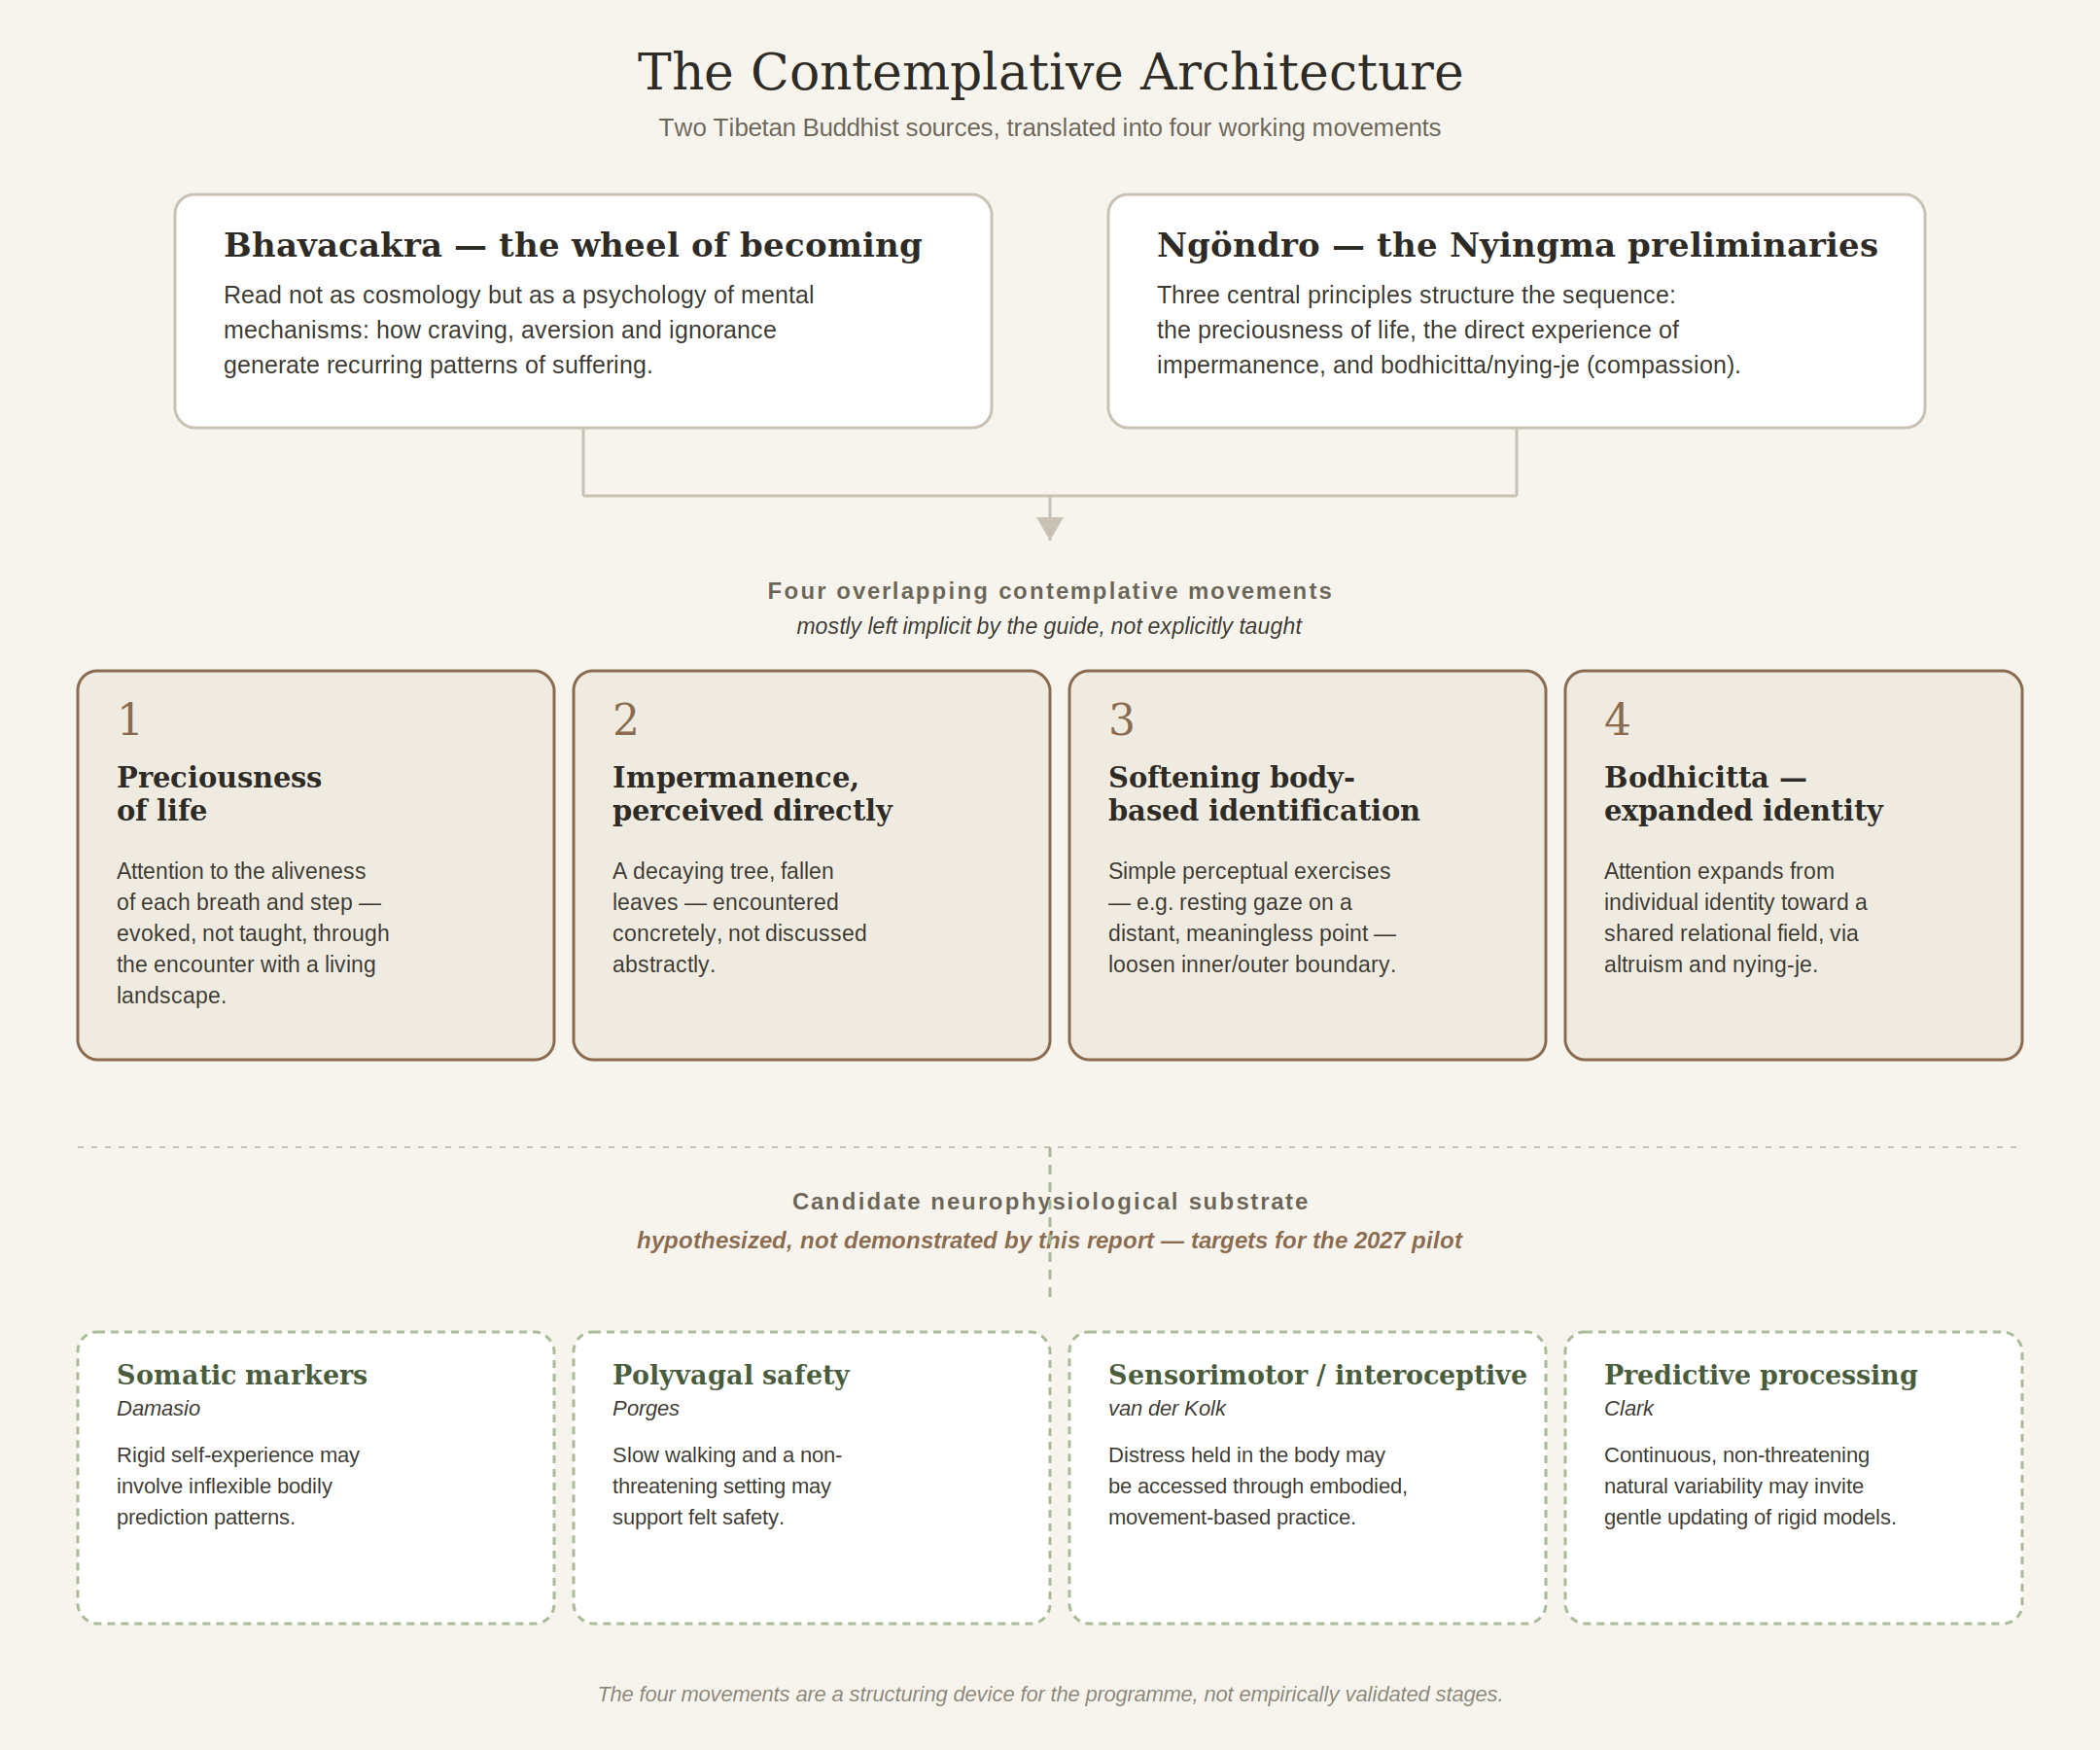
Mindtrek's conceptual framework draws on two elements of the Tibetan Buddhist tradition — the bhavacakra, read as a psychology of mental mechanisms rather than a cosmological map, and three central principles of the Nyingma school's ngöndro (the preciousness of life, the direct experience of impermanence, and the compassion-centered bodhicitta practice) — translated into secular, clinically accessible language.
In practice, this becomes four overlapping contemplative movements, mostly left implicit rather than explicitly taught: attention to the preciousness of life; direct perceptual encounter with impermanence; a gradual softening of body-based identification; and an expansion of attention from individual identity toward a shared relational field, cultivated through altruism and nying-je (compassion).
These four movements are a structuring device for the programme's sessions — a working architecture, coherent with a long-standing contemplative tradition — not a set of empirically validated stages.
Alongside this contemplative architecture, we propose four candidate frameworks. None is demonstrated by the present report, and they differ in standing.
First, Damasio's somatic marker hypothesis, according to which bodily signals may bias affective appraisal and decision-making. Its original evidence base, chiefly the Iowa Gambling Task, has been criticised; we retain only the general proposal that bodily states shape evaluation, and hypothesise that practices addressing bodily identification may alter how such signals are interpreted.
Second, predictive and interoceptive accounts (Clark; Seth), which belong to cognitive science and philosophy of mind rather than neurophysiology. Rigid self-experience may involve inflexible predictions about bodily states and the world. The continuous, non-threatening variability of a natural environment may generate low-intensity prediction errors that invite updating without a defensive response.
Third, embodied accounts of distress (van der Kolk), suggesting that movement-based practice may reach what verbal processing does not. We do not present Mindtrek as trauma therapy.
Fourth, Terror Management Theory. We treat mortality salience as an existential stressor intrinsic to cancer care, for patients and caregivers alike. Our own hypothesis, not a claim of the theory, is that where the self cannot loosen its contraction, this stress may become traumatic.
Note on Polyvagal Theory recent developments. Porges' Polyvagal Theory (2011) is currently the object of an open scientific dispute. A critical evaluation by Grossman and colleagues (2026) challenges its neuroanatomical, evolutionary and measurement premises, notably the interpretation of respiratory sinus arrhythmia as an index of vagal tone; Porges (2026) replies that the critique addresses a reconstruction rather than the theory as formulated. The authors do not take a position in this debate, and the present proposal does not depend on its outcome. Our interest is limited to autonomic regulation and perceived safety as functional constructs: the possibility that slow walking, shared silence and a non-threatening natural setting may support a felt sense of safety in participants who often begin the programme doubting their own adequacy. Any physiological measure (HRV) will be treated as a general autonomic marker, not as an index of vagal tone or of any specific vagal circuit. (See: Grossman P, et Al. Why The Polyvagal Theory Is Untenable: An international expert evaluation of the polyvagal theory and commentary upon Porges, S.W. (2025). Polyvagal theory: current status, clinical applications, and future directions. Clin. Neuropsychiatry, 22(3), 169-184. Clin Neuropsychiatry. 2026 Feb;23(1):100-112. doi: 10.36131/cnfioritieditore20260110. PMID: 41768017; PMCID: PMC12937499. and Porges SW. When A Critique Becomes Untenable: A Scholarly Response To Grossman Et Al.'S Evaluation Of Polyvagal Theory. Clin Neuropsychiatry. 2026 Feb;23(1):113-128. doi: 10.36131/cnfioritieditore20260111. PMID: 41768026; PMCID: PMC12937496.)
Mindtrek has been delivered as integrative therapy — not as a research study — in a collaboration with the Komen Italia Center for Integrative Oncology within the Fondazione Policlinico Universitario Agostino Gemelli, Rome, under a programme-based agreement renewed for each new cycle.
Two complete eight-week cycles have been conducted (winter 2025 and winter 2026), each involving breast cancer patients, their family caregivers, and a clinical team together. Clinical governance — including patient selection, informed consent, and care — rests entirely with the Gemelli medical staff, under the oversight of Claudia Maggiore.
The material gathered so far is experiential and qualitative in nature — real-world observations that point toward promising directions, motivating the more structured pilot below.
A structured mixed-methods pilot is planned for the programme's next cycle, winter 2027, incorporating the WHO-5 Well-Being Index and the PHQ-4 alongside continued qualitative data collection.